































































What Your Heart’s Structure Has to Do With Your Diagnosis
Stenosis. Blockage. Defect. If you’ve heard one of these words in a doctor’s office, it probably sounded like a foreign language, and the real questions tend to arrive after you’ve already left the room.
Here’s the reassuring part: nearly every one of those words is describing a part of the heart and what’s going wrong with it. A narrowed valve. A blocked artery. An opening that shouldn’t be there. That’s the connection between heart structure and diagnosis, and you don’t need a medical degree to follow it. You just need a map.
This guide builds on a basic tour of the heart’s structure and shows how each part connects to the conditions people are most often told they have, so your own diagnosis starts to make sense.
Why Your Diagnosis Is Really a Structure Question
So what is a diagnosis actually telling you? Almost always, it names two things: a part of the heart, and what’s wrong with it. Once you can place the part, the rest gets much easier to follow.
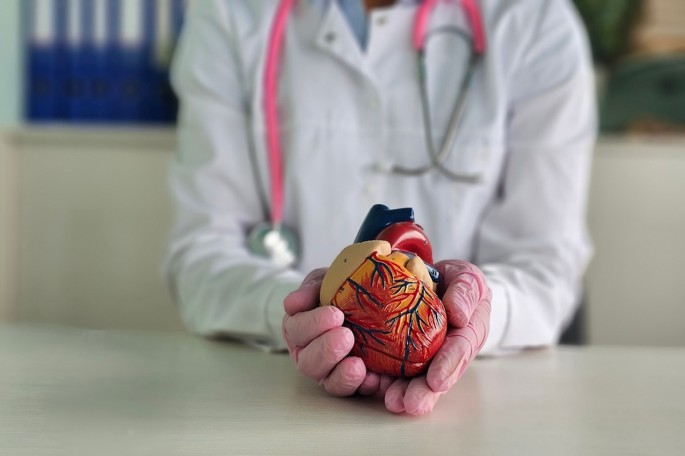
Here’s the quick version of the map. The heart has four chambers. The two upper chambers, the atria, receive blood, and the two lower chambers, the ventricles, pump it out. The right side sends blood to the lungs to pick up oxygen, and the left side sends that oxygen-rich blood out to the rest of the body. Four valves act like one-way doors between those spaces, keeping blood moving forward instead of back. The wall itself has three layers: a thin outer covering, a thick middle layer of muscle that does the pumping, and a smooth inner lining. And a set of vessels carries blood in and out, including the aorta, the large artery that sends blood to the body, and the coronary arteries, which feed the heart muscle itself.
That’s really it. When a doctor says a valve is narrowed, an artery is blocked, or a chamber has an opening it shouldn’t, they’re pointing to one spot on this map. Knowing which spot makes appointments less overwhelming, because you can follow the explanation instead of just nodding along. It also helps when a doctor pulls up an image or sketches a diagram, since you’ll know what you’re looking at and can ask better questions about the plan.
Our beginner’s guide to the heart’s structure goes deeper if you’d like a fuller refresher. For now, this is enough to start understanding your heart condition one piece at a time.
When the Problem Is a Valve
So what does it mean when your diagnosis points to a valve? Of all the places a heart problem can show up, valves are among the most common, which is why heart valve problems come up so often in diagnoses.
Quick reminder: you have four valves, the tricuspid, mitral, pulmonary, and aortic, and each one is a one-way door that opens to let blood through and closes to keep it from slipping back. Two of them, the aortic and mitral valves, work on the heart’s high-pressure left side, and they’re the ones most often needing surgical attention.
Valve problems usually come in two forms. A narrowed valve, known as stenosis, doesn’t open fully, so the heart has to work harder to push blood through. A leaking valve, known as regurgitation, doesn’t close fully, so some blood flows backward. Some valves have both problems at once. Either way, the diagnosis names the valve and names the problem, which is exactly the connection between heart structure and diagnosis we’ve been building toward.
Severity matters just as much as the type of problem. A mildly narrowed or leaky valve is often monitored over time, while a more severe one is more likely to call for treatment, which is why your imaging and follow-up measurements carry so much weight in the plan your doctor recommends.
From there, the question is usually repair or replace. Some valves, particularly the mitral valve, can often be repaired and kept in place, which many surgeons prefer when the valve allows it. Others need to be replaced, and replacement brings its own choice between mechanical and biological valves, which our page on choosing a biological or mechanical heart valve walks through.
Many of these procedures can be done through smaller incisions, depending on the valve and your case. If you want the specifics, we cover minimally invasive aortic valve surgery and minimally invasive mitral valve repair in more detail.
When the Problem Is the Heart’s Blood Supply
So what happens when the problem is the heart’s blood supply? The heart is a muscle, and like any muscle it needs a steady supply of oxygen-rich blood to keep working, every minute of every day. That supply doesn’t come from the blood flowing through its chambers. It comes from the coronary arteries, a network of vessels that branch off the aorta and wrap around the outside of the heart.
When those arteries narrow, usually from a gradual buildup of plaque, less blood reaches the muscle they feed. A partial blockage can cause chest pain or shortness of breath, especially during activity, because the muscle isn’t getting all it needs. A complete blockage can cut off the supply to part of the muscle altogether, which is what causes a heart attack. This is why a diagnosis of coronary blockage is really a statement about how well a specific section of heart muscle is being fed.
Treatment depends on how many arteries are affected, where the blockages sit, and how much muscle depends on them. In some cases, medication or stents are enough to restore good blood flow. In others, the answer is bypass surgery, where a surgeon uses a healthy blood vessel from elsewhere in the body to create a new route around the blocked section, like a detour around a roadblock. Minimally invasive coronary bypass surgery explains how that works through smaller incisions.
If bypass is what you’ve been told you need, here’s what actually happens next. Seeing a blockage as a structure problem, a section of muscle that needs a better supply, is a big step toward understanding your heart condition and the choices in front of you.
When the Problem Is a Chamber, Opening, or Major Vessel
Some diagnoses don’t involve a valve or an artery at all. They involve a chamber, an opening that shouldn’t be there, or the wall of the body’s largest blood vessel. Here’s how three of them connect back to the structure you just read about.
An atrial septal defect, or ASD, is an opening in the wall between the heart’s two upper chambers, which lets blood cross to the wrong side and makes the right side of the heart work harder than it should. Some people are born with one, and others learn about it later in adulthood.
An atrial myxoma is a tumor that grows inside one of those upper chambers, and because pieces can break loose and travel, it is usually removed promptly. Atrial myxoma surgery explains how the tumor and the section of wall it grows from are taken out.
An aortic aneurysm is a weakened, bulging section of the aorta, the major vessel that carries blood out of the heart to the rest of the body, and the wider it grows, the greater the risk that the wall can tear or rupture.
Each one is a different structure with a different problem. Once you know which chamber, opening, or vessel is involved, the diagnosis stops being a string of unfamiliar words, and the connection between heart structure and diagnosis becomes something you can use when you talk with a surgeon.
Questions That Help Your Diagnosis Make Sense
You don’t need a medical degree to follow your own diagnosis. You just need the right questions. Understanding your heart condition is part of your care, and it starts with what you ask. Doctors use shorthand all day, so it’s easy to nod along without following. Bring these to your next appointment, and don’t hesitate to ask for plain language.
- Which structure is involved? Ask your doctor to name the exact part: a specific valve, an artery, a chamber, or the aorta. “A heart problem” isn’t a complete answer.
- What exactly is wrong with it? Is it narrowed, leaking, enlarged, blocked, or open where it should be closed? The structure tells you where the problem is, and this tells you what kind of problem it is.
- How severe is it? Ask whether it’s mild, moderate, or severe, and what that means for your symptoms. Severity often decides whether you need treatment now or careful monitoring.
- What does the imaging show? Ask to see your echocardiogram, angiogram, or CT scan, and have your doctor point to the problem area. Seeing it on the screen can make everything click.
- Should it be repaired or replaced? Repair means fixing the structure you have, and replacement means swapping it out. The right choice depends on your case, so ask which one fits and why. Ask what each option means for your recovery and how long the result lasts.
Write the answers down, or bring someone along who can. If something still doesn’t make sense, ask again. A good surgeon will explain it as many times as it takes, and a second opinion is a reasonable step if the answers you’re getting don’t leave you confident in the plan.
Quick Answers
What is a heart diagnosis actually telling you?
A diagnosis usually names two things: a part of the heart and what’s wrong with it. Once you can place that part on the map of chambers, valves, wall layers, and vessels, the rest of the explanation gets much easier to follow.
Which parts of the heart can a diagnosis point to?
The four chambers, the four valves, the three layers of the heart wall, and the vessels that carry blood in and out, including the aorta and the coronary arteries.
What’s the difference between a narrowed valve and a leaking valve?
A narrowed valve, called stenosis, doesn’t open fully, so the heart works harder to push blood through. A leaking valve, called regurgitation, doesn’t close fully, so some blood flows backward. Some valves have both problems at once.
What does a blocked coronary artery mean for the heart?
It means part of the heart muscle isn’t getting all the blood it needs. A partial blockage can cause chest pain or shortness of breath, and a complete blockage can cause a heart attack. Treatment depends on how many arteries are affected and where.
What should I ask my doctor to understand my diagnosis?
Ask which structure is involved, what exactly is wrong with it, how severe it is, what the imaging shows, and whether it should be repaired or replaced. Writing the answers down helps.
•••
If your diagnosis still feels like a foreign language, you don’t have to work it out alone. You’ve already done the hardest part by learning how the heart is put together. The next step is a conversation, and it can start with a simple question: which part of my heart is involved, and what does that mean for my options?
Dr. Giovanni Ciuffo is the Director of Cardiac Surgery at University Medical Center of Southern Nevada, and he runs a national referral practice, so patients travel to Las Vegas from across the country for a second opinion or a clearer plan. If you’d like to talk through your own case, you can request a heart surgery consultation in Las Vegas. Bring your imaging and your questions, and we’ll start with the map.
Apa Reaksi Anda?
 Suka
0
 Kurang Suka
0
 Setuju
0
 Tidak Setuju
0
 Bagus
0
 Berguna
0
 Hebat
0








