

































































Less paperwork, more medicine: Practicing in an integrated care system

How integrated care reduces paperwork, documentation demands, coding distractions, and referral friction — giving physicians more time and space for patient care
By Brent Johnson
The Permanente Federation
In private practice, Jess Holzman, MD, managed a panel of 2,800 patients. Friday was theoretically her day off, but work often continued at home. “Every Thursday night, I would bring home a manila envelope with a stack of paperwork,” she says.
That envelope included all kinds of tasks, including prescription refills. Each request could require comparing pharmacy options, entering prescription information, confirming dosage, checking laboratory results, and reviewing blood pressure readings. Repeated across hundreds of patients, the work consumed hours each week.
For many physicians in fragmented, fee-for-service systems, administrative work is simply part of each day: signing forms, authorizing prescriptions, selecting billing codes, locating records in separate systems, and following up on referrals.
Individually, these tasks may appear routine. Together, they can interrupt clinical reasoning, extend the workday, and shift attention from patient care to administrative and financial considerations.
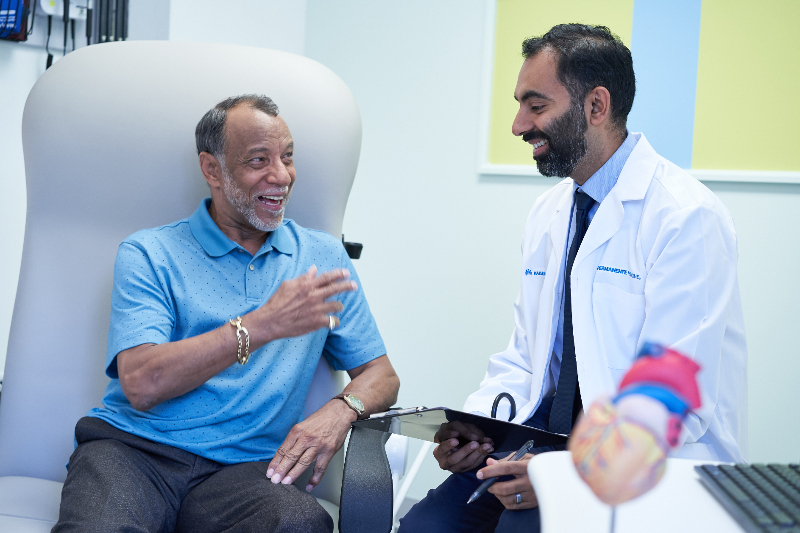
The physicians in this story describe how those daily demands are shaped by the system they practice in — and how they change when coverage, facilities, clinicians, pharmacists, and specialists work within an integrated, value-based care model like Kaiser Permanente.
After Dr. Holzman joined Northwest Permanente to practice family medicine, much of that paperwork went away. “To have it vaporize instantaneously was absolutely lovely,” she says.
Related story: What is Permanente Medicine?
How team-based prescription refills reduce after-hours work
Dr. Holzman now works closely with pharmacists using agreed-upon protocols that allow most routine refill requests to be completed without a physician reviewing each one.
Because Kaiser Permanente operates its own pharmacies, patients and physicians can avoid multiple layers of review, streamlining the process and speeding medication delivery.
“Now, 85% of our refills are done via protocol,” Dr. Holzman says. “I only do 15% of my own refills, which is absolutely fantastic.”
Elizabeth Buys, MD, an OB-GYN at The Permanente Medical Group in Northern California, describes a related change in her daily work: fewer gaps in patient information and less time spent thinking about billing codes.
How connected patient records lighten the cognitive load
For more than two decades, Dr. Buys practiced in a for-profit hospital system in North Carolina, where caring for patients often required gathering information from disconnected sources.
For a high-risk patient, she might review hundreds of pages of scanned or faxed records from multiple locations — if those records arrived at all.
“In those situations, you just know you’re missing something,” Dr. Buys says. “And that’s a terrible feeling.”
After joining Kaiser Permanente in 2024, Dr. Buys found that the vast majority of her patients’ paperwork was neatly arranged in a shared electronic health record, reducing the need to reconstruct a clinical history from separate files.
She also experienced another form of relief — from coding.
Coding to document care — not maximize payment
In the nation’s fragmented care system, medical coding helps health care providers, insurance companies, and government programs determine reimbursement. Physicians may therefore need to consider not only which code reflects an encounter, but also whether their documentation supports the level of payment associated with it.
“Coding was hard” at her former hospital, Dr. Buys says. “I was always wondering what code to put down — 1, 2, or 3? Do I need to document this one more thing so that it would actually be a 3? That was a decision I had to make every time I saw a patient.”
At Kaiser Permanente, care delivery, coverage, and facilities operate within an integrated model. Permanente physicians are not paid according to the code selected for each individual encounter; instead, they’re aligned with agreed-upon incentives in a value-based care model.
For Dr. Buys, that means coding can return to its clinical purpose: documenting the care she provides. Nothing more.
“It just opened up this opportunity to have that thinking go into something else much more important — my patients, not someone’s bottom line,” Dr. Buys says. “It lifted a cognitive burden that always occupied my mind.”
Integrated specialty care streamlines referrals
Referrals create another daily challenge in fragmented systems. When a specialist is difficult to reach, the referring physician may be left managing clinical uncertainty while the patient waits.
“When you think a patient needs to go see a neurologist, but that appointment isn’t available for 8 months,” she says, “then you’re stuck telling the patient what you think is really important, but they can’t do anything about it.”
Kellen Galster, MD, an emergency medicine physician with The Permanente Medical Group, remembers working with the same uncertainty prior to joining Kaiser Permanente.
In his former practice settings, the hospitals, physicians, and specialists all operated independently. A referral could mean sending a patient into another system without a direct way to coordinate next steps.
His current experience is different. “I can pull up my smartphone and call any specialist,” Dr. Galster says. “The stress is so much less, and my feel-goods are so much higher just knowing that I’m able to contact anyone.”
Within Permanente Medical Groups, specialists often practice in the same medical facilities and on shared systems as primary care physicians. That structure can make consultation and coordination more direct.
Instead of sending a patient to see a specialist in a disconnected care system and hoping for the best, Dr. Galster can bring a specialist into the conversation and make better, more informed decisions.
“It allows me to advance care for the patient and have more reassurance that we’re doing the best possible thing,” Dr. Galster says. “That quality of care and attention meets patients where they need to be met.”
What a physician’s day can look like in an integrated care system
In fragmented, fee-for-service settings, the administrative burdens these physicians describe are often treated as unavoidable features of practicing medicine.
But as Drs. Holzman, Buys, and Galster can attest, practicing in an integrated, value-based system not only reduces the coordination physicians must carry themselves, it also provides more time and space to focus on clinical judgment, collaboration, and continuity of care.
For prospective physicians considering how to get back to the essence of practicing medicine, Dr. Galster offers the following:
“What brought me to Kaiser Permanente was their quality benchmarks and the quality of outcomes for their patients,” he says. “And I wanted to be part of that system.”
The post Less paperwork, more medicine: Practicing in an integrated care system appeared first on Permanente Medicine.
Apa Reaksi Anda?
 Suka
0
 Kurang Suka
0
 Setuju
0
 Tidak Setuju
0
 Bagus
0
 Berguna
0
 Hebat
0












